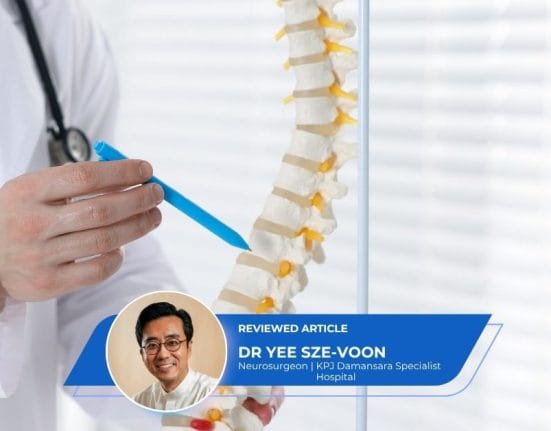
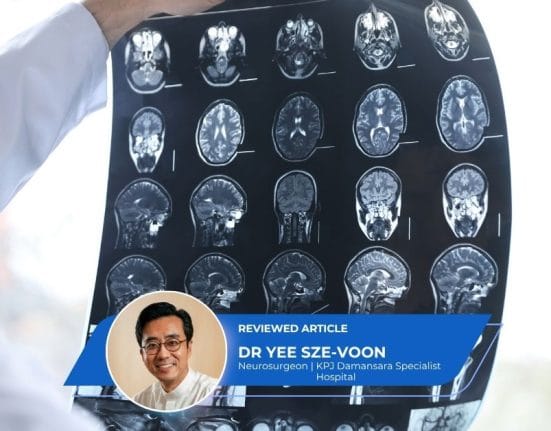
Sciatica is not a standalone medical condition; it is a clinical symptom pattern usually caused by irritation or compression of one or more lumbosacral nerve roots. These nerve roots contribute to the sciatic nerve, which runs from the lower back through the buttocks and down each leg. When these nerve roots are irritated or compressed, they can cause sharp, shooting, burning, or aching sensations that radiate from the lower back or buttock into the leg.
Sciatica can cause significant pain and functional impairment, particularly when symptoms interfere with walking, sitting, work, or everyday activities. Recognising the primary causes and understanding when conservative management versus emergency medical evaluation is required is essential for protecting nerve function and maintaining mobility.
Back To: Brain and Spine Care Main Page
Causes of Sciatica
Sciatica typically occurs when an underlying spinal pathology affects the nerve roots exiting the lumbar or sacral spine.
Pathological Pathway:
Lumbosacral Spine Pathology → Nerve Root Irritation or Compression → Radiating Leg Symptoms
- Herniated Discs (Slipped Discs): The gel-like centre of an intervertebral disc bulges or tears through its outer ring, directly irritating adjacent lumbosacral nerve roots.
- Spinal Stenosis: The narrowing of the spinal canal or intervertebral foramina, commonly caused by age-related bony spurring or ligament thickening in older adults.
- Spondylolisthesis: The forward slipping of one vertebra over another, causing narrowing of the channels through which spinal nerves exit.
- Degenerative Disc Changes: Age-related changes in the intervertebral discs can contribute to loss of disc height and narrowing of the spaces available for spinal nerves.
- Piriformis Syndrome: A less common, non-spinal cause where the piriformis muscle deep in the buttock tightens or spasms, irritating the nearby sciatic nerve.
Triage & Red Flag Symptoms
While the majority of sciatica episodes improve with time and activity modification, severe compression of the nerve roots in the lower spinal canal can, in rare cases, cause a medical emergency known as Cauda Equina Syndrome (CES). CES occurs when the bundle of nerve roots at the base of the spinal cord becomes critically compressed.
Triage Overview
- Typical Sciatica Symptoms: Unilateral pain, tingling, or numbness with preserved bowel and bladder function. Often managed initially with staying active as tolerated and other conservative treatments.
- Cauda Equina Syndrome / Emergency Red Flags: Saddle sensory loss, bladder/bowel dysfunction, bilateral sciatica, or rapid motor loss. Requires immediate emergency medical triage.
Critical Red Flags Requiring Immediate Emergency Evaluation:
- Saddle Anaesthesia: Loss of sensation or numbness around the perineum, buttocks, inner thighs, or genital area.
- Bowel or Bladder Dysfunction: Sudden difficulty passing urine (retention), inability to feel when the bladder is full, or uncharacteristic loss of bowel or bladder control (incontinence).
- Bilateral Sciatica or Severe Bilateral Neurological Symptoms: Sciatic symptoms affecting both legs, particularly when accompanied by severe or worsening numbness or weakness.
- Progressive Motor Deficits: Rapidly worsening weakness in the lower limbs, such as “foot drop” (inability to lift the front of the foot) or sudden inability to bear weight.
Other Warning Signs Requiring Prompt Medical Assessment
Other symptoms that warrant prompt medical assessment include sciatica associated with significant trauma, unexplained fever or a history of cancer, as these may indicate another serious underlying condition.
Diagnostic Pathways in Malaysia
When consulting a medical professional in Malaysia, diagnosis involves a thorough physical examination supported by selective imaging when clinically indicated:
- Clinical Assessment & Physical Exam: Includes nerve stretch tests (such as the Straight Leg Raise) and neurological evaluations testing dermatomal sensation, muscle strength, and deep tendon reflexes.
- Magnetic Resonance Imaging (MRI): MRI is not routinely required for uncomplicated sciatica at initial presentation. It is considered when serious underlying pathology is suspected, when neurological symptoms are severe or worsening, or when imaging is needed to guide targeted procedures or surgical planning.
- X-rays & CT Scans: Used selectively to evaluate bone alignment, severe spondylolisthesis, or structural skeletal changes.
Non-Surgical Treatment Options
Many episodes of sciatica gradually improve over a period of several weeks to a few months without invasive intervention.
| Treatment Category | Clinical Guidance & Interventions | Purpose & Considerations |
| Pharmacotherapy | Short-term NSAIDs may be considered for select patients. Note: Gabapentinoids are not recommended for routine treatment of sciatica because evidence has not shown an overall benefit and there is evidence of harm. | NSAIDs should be used at the lowest effective dose for the shortest necessary duration, taking into account individual cardiovascular, gastrointestinal and kidney-related risks. |
| Physical Therapy & Activity | Staying active as tolerated, structured gentle exercises, core stabilisation, and general physiotherapy. | Encourages movement, avoids the harms of prolonged bed rest, and supports spinal biomechanics. |
| Manual Therapy | Gentle spinal mobilisation or soft-tissue techniques alongside an exercise programme. | May offer short-term symptomatic relief when integrated into a broader active recovery plan. |
| Epidural Steroid Injections | Targeted corticosteroid injections near the affected nerve root. | May be considered for acute and severe sciatica when appropriate. |
Surgical Options for Persistent Sciatica
Surgery is not automatically triggered by a specific calendar timeframe. Instead, spinal decompression is considered when non-surgical treatments have not adequately improved pain or daily function, and radiological findings are consistent with the patient’s symptoms and clinical findings. Rapidly progressive neurological deficits or suspected Cauda Equina Syndrome require urgent surgical evaluation.
- Microdiscectomy: A targeted procedure to remove the specific portion of herniated disc material irritating the nerve root.
- Spinal Decompression (such as Laminectomy): Removal of bone or other tissue contributing to nerve compression, depending on the underlying cause.
- Minimally Invasive Spine Surgery (MISS): Techniques utilising smaller incisions and specialized instruments to reduce soft-tissue disruption where clinically suitable.
Neurosurgeons in Malaysia You May Consider
Choosing the right specialist is a critical step in your recovery. Some Neurosurgeons in Malaysia that you may consider for diagnosis and treatment:


Featured Doctor - Dr Yee Sze-Voon
For inquiries or for an introduction to a specialist, contact us below.
Frequently Asked Questions (FAQs)
1. How long does a typical episode of sciatica last?
Sciatica often improves over several weeks to a few months. Recovery times vary depending on the underlying cause and individual health factors. Staying active within comfortable limits and following guided physical exercises may support recovery.
2. Should I rest in bed if I have sciatic pain?
Prolonged bed rest is generally not recommended for sciatica. Remaining as active as tolerated and continuing normal daily tasks within pain limits promotes better functional outcomes than staying inactive in bed.
3. What is the main difference between general back pain and sciatica?
General back pain is usually localized strictly to the lumbar region, soft tissues, or spinal joints. Sciatica involves nerve-root irritation that can cause pain, numbness or tingling extending from the lower back or buttock into the leg, sometimes below the knee.
4. Is massage therapy or chiropractic treatment safe for sciatica?
Manual therapies, including massage or mobilisation, may be considered as part of a broader management plan that includes exercise. However, suitability depends on the individual’s diagnosis and neurological status, and anyone with severe pain, progressive weakness, or red flag symptoms should seek formal medical evaluation first.
5. When should I seek emergency medical care for sciatica?
You should proceed immediately to the nearest emergency department if your symptoms include numbness around your groin/buttocks (“saddle anaesthesia”), sudden loss of bladder or bowel control, inability to pass urine, or severe, rapidly worsening weakness in one or both legs.

This medical content has been reviewed by Dr Yee Sze-Voon, a Consultant Neurosurgeon specialising in brain and spine surgery, minimally invasive procedures, and pain management. His commitment to precise diagnosis and patient-centred care makes him a trusted specialist for comprehensive neurological health.
All content on this site is informative only and is not intended to be a substitute for professional medical advice,
diagnosis, or treatment, and should never be relied upon for specific medical advice.
If you are experiencing a medical emergency, call 999 immediately or go to the nearest Accident & Emergency department.
365Asia is a member of Group 365Asia.